
Community Health Nursing Dissertation Topics: Narrow Ideas From District Nursing to Health Visiting

Questions to Settle Before Choosing a Community Health Nursing Dissertation Topic
Community health nursing dissertation topics work best when they pin down one nursing role, one setting and one question you can answer with evidence you can actually reach. A broad idea such as “health promotion in the community” gives you a theme. A title that names a role, a policy and a data source gives you a proposal.
You have probably chosen your degree already, so the real task is narrowing. Settle these questions first:
- Which community role am I studying: district nursing, general practice nursing, health visiting, school nursing or community children’s nursing?
- Am I asking about people’s experience, how a service performs, or what a policy change did?
- Can I reach my evidence without NHS ethics approval, or should I build a review or a secondary-data project?
- Does my idea rely on England-only policy, or can I frame it for the country where I will practise?
- Which people could my method leave out, such as housebound patients, carers or people who need an interpreter?
- What would I remove first if my supervisor says the scope is too big?
Scope: this resource covers nursing delivered in people’s homes, general practice, schools, care homes and neighbourhood teams. In the UK, the regulated routes are specialist community public health nursing (health visiting, school nursing and occupational health nursing, set out in the NMC standards of proficiency for specialist community public health nurses) and community nursing specialist practice qualifications such as district nursing. Population-level programmes sit better with public health nursing dissertation topics, while hospital-based children’s care belongs with child health nursing dissertation topics. Workplace services have their own set of occupational health nursing dissertation topics. Here, the focus stays on the community nurse’s role.
Position correct as of October 2026. Policy in this field moves quickly. Neighbourhood health in England, community waiting list figures and the second phase of Awaab’s Law (due from 30 November 2026) may change before you submit, so check NHS England, GOV.UK and your university’s guidance before you fix a title. Where an idea depends on England-only policy, the explanation says so, and you can adjust the context to your own country.
Level tags show where each idea fits. Undergraduate ideas are explained in plainer terms and often suit a literature-based project. Master’s and PhD ideas assume primary data, secondary datasets or a comparative design.
District Nursing and Community Nursing Teams: Complex Care at Home
The James Lind Alliance community nursing top ten ranked the most important unanswered questions from patients, carers and nurses. Several ideas below turn those priorities into projects. For hospital-focused ideas, try adult nursing dissertation topics instead.
1. How community nurse teams meet the complex needs of people living with several long-term conditions, using priority 1 of the James Lind Alliance top ten as the research question
The partnership ranked this question first, yet “complex needs” can mean frailty, multimorbidity or social complexity. A Master’s student could interview district nurses and patients in one team and ask how each group defines complexity. An undergraduate could run a scoping review that compares definitions across community studies. If patients take part, expect NHS ethics review (see the ethics notes below).
2. Whether seeing the same community nurse over time changes quality of care (priority 7), measured through visit records rather than patient opinion alone
Continuity is easy to praise and hard to measure. You could build a simple continuity measure from visit schedules, then compare it with outcomes such as unplanned admissions in one service. Because routine records contain identifiable data, check data-sharing rules early. A review-only version works well at undergraduate level.
3. How community nurses share care with patients and family carers, such as teaching a carer to change a dressing (priority 2), and where accountability sits if the carer makes an error
Qualitative interviews with nurses and carers could map which tasks are handed over and what safety nets exist. Then compare your findings with the dignity and accountability duties in the International Council of Nurses Code of Ethics (2021). This suits a Master’s project.
4. How community nurse teams contribute to managing acutely ill patients at home, and what that does to hospital admissions (priority 3), compared across two services
A Master’s design could compare two community trusts that use different acute-response models. Hospital Episode Statistics are the usual admissions source in England, but access takes time. An undergraduate version should therefore rely on published service evaluations.
5. How community nurse teams and social care providers communicate during one hospital discharge pathway (priority 5), studied through document analysis and interviews
Start with discharge letters, referral forms and care plans, then interview nurses and social workers to test what the documents miss. NICE guideline NG27 on transitions between hospital and community or care home settings gives you a standard to judge them against. Anonymise every document before it enters your analysis.
6. Which pandemic-era changes to community nursing, such as timed visits and working from home, teams chose to keep (priority 6), and the reasons they gave
Because teams made these decisions locally, a case study of two services would capture real variation. Use a short interview guide and our thematic analysis guide to code the answers. Rely on teams’ own records as well as memory.
7. How community nurses involve unpaid carers in decisions about a loved one’s care (priority 4) when the patient has capacity and has asked for information to stay private
The tension between confidentiality and carer involvement shows up daily. The Care Act 2014 sets duties towards carers in England, so a policy analysis of those duties alongside nurse interviews would fit a Master’s project. Include at least one scenario where the carer and patient disagree.
8. Whether the district nurse specialist practitioner qualification changes how team leaders describe their clinical decision-making, building on the Queen’s Nursing Institute’s 2019 report on district nurse team leaders
The report District Nursing today gathered views from team leaders across the UK. A smaller project could interview team leaders with and without the qualification and compare how each explains triage and delegation. Treat any differences as descriptions, not proof that the qualification caused them.
9. How lone-working community nurses decide whether a late visit is safe to make, using the critical incident technique
Ask nurses to describe one specific visit where they felt unsafe, what they weighed and what they did. This keeps answers concrete. Employer policies differ, so compare two employers’ lone-working procedures rather than assuming one national rule.
Urgent Community Response, Virtual Wards and Hospital at Home
NHS England guidance describes virtual wards as acute care, monitoring and treatment delivered at home, usually for up to 14 days, in place of a hospital stay. NHS England’s virtual ward guidance describes two pathways, acute respiratory infection and frailty (hospital at home), and community nurses sit at the centre of both.
10. Whether the national objective for 70% of urgent community response referrals to be seen within two hours shapes how triage nurses prioritise referrals
Reports from 2024 show trusts meeting the objective nationally, so the more interesting question is what behaviour sits behind the number. Interview triage staff, then pair their accounts with the published urgent community response data. Check the current standard before you write, because targets change with each planning round.
11. How community nurses and allied professionals divide responsibility on a frailty virtual ward during the first 14 days of care
A qualitative case study of one frailty ward could map who monitors, who prescribes and who escalates. Include a diagram of the escalation route in your findings. The case study will describe one service, so avoid claiming it speaks for all of them.
12. How family carers experience remote monitoring on a technology-enabled virtual ward, including the extra tasks it asks of them
Carers often take readings, charge devices and call for help. Interviews can show whether monitoring reassures them or adds a second job. NHS England publishes guidance on choosing technology platforms for virtual wards, which helps you describe the equipment carers handled.
13. How closely the Skills for Health capabilities framework for virtual wards matches what community nurses say they do each day
Match each capability against interview accounts and note gaps in both directions. This suits a Master’s project because it needs careful coding. An undergraduate could complete the document half as a critical appraisal.
14. Which people are excluded from technology-enabled virtual wards, and what community nurses do for them instead
Exclusion may follow from housing, language, disability or poor connectivity. A review of published virtual ward evaluations could ask who was eligible and who was recorded as declining. Compare what you find with NHS England’s operational guidance for the model.
15. What the rapid evidence synthesis on virtual wards and older people by Norman and colleagues in Age and Ageing leaves unanswered for nursing outcomes
A critical appraisal suits an undergraduate who cannot collect primary data. List the outcomes the synthesis reports, then note nursing-sensitive outcomes it does not cover, such as pressure injuries or carer strain. Finish with two research questions that would fill the gap.
Neighbourhood Health and Community Health Nursing Policy in England
The 10 Year Health Plan for England, published in July 2025, set out three shifts: hospital to community, analogue to digital and sickness to prevention. The government then announced a Neighbourhood Health Framework in March 2026, and local systems are building integrated neighbourhood teams. These policies apply to England only, because the other UK nations set their own health plans.
16. What the community nurse role looks like inside integrated neighbourhood teams that cover roughly 30,000 to 50,000 people, according to the Neighbourhood Health Framework
The framework positions these teams as the main way neighbourhood health will be delivered. A document analysis of three local plans could compare how each describes nursing work, leadership and caseloads. Because the framework sets a direction rather than a template, expect wide variation.
17. Whether the six core components in NHS England’s Neighbourhood Health Guidelines 2025/26 appear in community nursing job descriptions and service specifications
The components are population health management, modern general practice, standardising community health services, neighbourhood multidisciplinary teams, integrated intermediate care with a Home First approach, and urgent neighbourhood services. Collect documents from two integrated care boards and code them against that list.
18. What authority and resources proposed neighbourhood nursing and midwifery leads would need to coordinate strategy across several neighbourhoods
The 10 Year Health Plan proposes these leads, so the role is still taking shape. Frame the question around the enduring issue of authority rather than one local job title. A Delphi study with senior community nurses suits a Master’s project, though recruiting enough experts takes time.
19. How standardising community health services, one of the six core components, can sit alongside local flexibility, tested through two contrasting trusts
Standardisation may help equity but may also override what works locally. Compare service specifications, then interview service managers. Keep the claim modest: you are describing how managers reconcile the two, not judging which approach is right.
20. Which community services have driven the rise in community health service waiting lists, where adult lists grew by 23% and children and young people’s lists by 58% between October 2022 and July 2025
Nuffield Trust analysis found that a small number of service types account for most of the growth. Use the NHS England waiting list data to test whether nursing-led services follow the same pattern. A time-series chart plus a short discussion suits a Master’s project, and health economics dissertation topics offer ideas for costing the delay.
21. How people waiting for nursing support for continence or colostomy care, about 5% of the adult community waiting list in July 2025, describe the effects of waiting
Few studies hear from this group. Interviews with patients would need NHS ethics review, so a document analysis of Healthwatch reports may be the practical option for a student project. Either way, handle the topic sensitively.
22. How integrated neighbourhood teams identify housebound people who are not yet known to services, one of the Neighbourhood Health Framework’s early priority groups
The framework’s early focus includes frailty, care home residents, housebound people and people near the end of life. A mixed-methods case study could combine practice-list data on housebound status with interviews about how teams find people who fall outside registers. Define “housebound” before you begin, since services use different definitions.
23. How accountability should be shared between registered community nurses and community health workers or volunteers in neighbourhood teams, as the 10 Year Health Plan describes
The plan’s neighbourhood teams include community health workers and volunteers. A vignette study could ask nurses and managers who is accountable when a non-registered worker raises a concern. The NMC Code and employer policies will shape the answers, so cite both.
24. What the nurse consultant role adds to neighbourhood health teams, which the 10 Year Health Plan describes as providing advanced clinical care and system leadership
Compare the plan’s wording with a small set of nurse consultant job plans, then interview post-holders. This suits a PhD or professional doctorate better than a taught Master’s, because access to senior participants takes time.
Long-Term Conditions, Wounds and Foot Care: Community Nursing Research Ideas
Wound and foot care fill many district nursing visits. For clinical depth beyond the community angle, see wound care nursing dissertation topics.
25. How consistently community nursing services complete a pressure ulcer risk assessment at the first face-to-face visit, as statement 2 of NICE quality standard QS89 expects
The standard defines a numerator and a denominator, so you can design a records review that mirrors it. Check whether your university treats the work as audit or research before you start. A smaller undergraduate version could review published audits of the same measure.
26. How district nurses teach and supervise family carers in pressure area care, and what carers say they still do not know
Pressure ulcer prevention depends on repositioning and skin checks between visits. Ask carers what they were shown, by whom and how often. Then compare their accounts with the advice on patient and carer information in NICE guideline CG179.
27. Whether long waits for podiatry, about 13% of the adult community waiting list in July 2025, delay foot protection for people with diabetes, set against NICE guideline NG19’s call for a community foot protection service
The question joins two data sources: waiting list data and foot protection service coverage. A Master’s student could map both at integrated care board level and describe how well they match. Do not claim waits cause ulceration, because NG19 and the waiting data cannot show that.
28. How district nurses apply foot risk categories when assessing housebound people with diabetes at home
Housebound people may miss clinic-based foot checks. Observation of home assessments, with consent, plus short interviews would show how nurses adapt checks to a living room or bedroom. The NG19 risk assessment recommendations give you the benchmark.
29. How community nurses raise uptake of COVID-19, flu and pneumonia vaccines among people with COPD in the most deprived 20% of neighbourhoods, which Core20PLUS5 names as a focus for chronic respiratory disease
Core20PLUS5 asks systems to drive vaccine uptake in COPD to cut infective flare-ups and emergency admissions. A service evaluation in one practice cluster could compare outreach methods. Use local deprivation data to define the Core20 areas.
30. How community nurse-led blood pressure checks reach groups that routine practice screening misses, linked to Core20PLUS5 hypertension case-finding
Look at where checks happen: homes, pharmacies, faith centres or day centres. A small pilot evaluation could count who attended and who was missing. Present results descriptively unless you have a comparison group.
31. How much district nurse visit time goes on insulin administration for people with type 2 diabetes who cannot inject themselves, and what alternatives teams have tried
Measure with a time-and-motion approach in one team, with the team’s agreement and anonymised records. The result would inform debates about scarce visiting capacity. Treat it as one team’s picture, not a national estimate.
32. Why some people stop compression therapy for venous leg ulcers at home, explored through interviews with patients and the nurses who treat them
Adherence is often framed as a patient problem. Interviews may show that comfort, mobility, footwear and visit timing play a part. Report both groups’ views side by side so readers can see where they differ.
33. How people living with heart failure define a good day at home, and whether nurse-led self-management support aims at the same outcomes
Compare patient-defined outcomes with the targets in service protocols. A qualitative design with a small purposive sample suits a Master’s project. Undergraduates can review qualitative heart failure studies to do similar work.
34. How people who use intermittent self-catheterisation learn the technique from community nurses, and which parts of the teaching they remember at home
Teaching often happens once and is then tested alone in a bathroom. Interviews a few weeks later can show what stuck. Because the topic is sensitive, plan a distress protocol and a clear way for participants to withdraw.
Frailty, Falls, Care Homes and End-of-Life Care at Home
NICE published guideline NG249 on falls assessment and prevention on 29 April 2025, replacing CG161. It covers people aged 65 and over and people aged 50 to 64 at higher risk. Related ideas for older patients appear in geriatric nursing dissertation topics.
35. How community nursing teams have replaced falls risk scores with comprehensive falls assessment since NICE guideline NG249 told practitioners not to use falls risk prediction tools
NG249 recommends individual assessment rather than risk scores. Interviews with team leaders, plus a review of assessment forms before and after April 2025, could show what changed in practice. Keep the time frame short, since implementation is still under way.
36. How community nurses decide whom to refer to falls prevention exercise programmes when a person has fallen and has a gait or balance problem
NG249 identifies this group as the one to offer an exercise programme. In practice, referral depends on local programme capacity, transport and the person’s willingness. A mixed-methods study could compare referral rates with waiting times for local classes.
37. How community nursing teams and primary care networks share duties under the Enhanced Health in Care Homes framework, revised in November 2023 as guidance on proactive care for people living in care homes
The framework supports the minimum standard in the Network Contract Directed Enhanced Service and the NHS Standard Contract. Compare what it requires with what two care homes report receiving. Care home participants may be vulnerable, so plan consent carefully.
38. Whose job it is to notice early deterioration in care home residents: a study of nurses employed by homes and community nurses who visit them
Boundaries blur when visiting nurses rely on care assistants’ observations. Interviews with both groups could map who spots what. A short vignette about a resident with a new cough can anchor the conversation.
39. How intermediate care nurses apply the NICE NG74 recommendation to offer reablement as the first option for people being considered for home care
Reablement aims to restore independence, yet pressure on beds can push teams straight to home care. A case study of one intermediate care service could compare referral records with the guideline’s advice. It overlaps with rehabilitation nursing dissertation topics, so keep your focus on the community nurse’s role.
40. How community nurses use the ReSPECT process, launched in 2016 by the Resuscitation Council UK, in conversations with people in the last year of life
ReSPECT is now the main emergency care and treatment planning approach across much of England and parts of Scotland. Interviews with nurses could ask when they raise it and what stops them. An NIHR-funded evaluation has already studied implementation, so show clearly what your project adds.
41. How community nurses and family carers manage anticipatory “just in case” medicines at home during the last days of life
Carers can feel unsure about what to give and when. Interviewing carers after a death needs careful ethics approval, so a safer undergraduate option is a review of published carer experience studies. More end-of-life ideas sit in palliative care nursing dissertation topics.
42. How overnight community nursing services support people dying at home, and whether families know the service exists
Night services vary by area. A mapping exercise of services in two regions, followed by short interviews with bereaved relatives where ethics permits, would give both coverage and experience. Report coverage as a descriptive map rather than a ranking.
43. What bereaved carers say about community nursing contact in the weeks after a home death
Bereavement support is often left to the GP or a hospice. A qualitative study with a small number of carers, recruited through a hospice or voluntary group, needs sensitive timing and a clear support plan.
44. How district nurses experience hospital discharge information, judged against the items listed in NICE guideline NG27
Compare what discharge summaries contain with what NG27 recommends. A document audit of a small set of anonymised summaries could be paired with a few interviews. Ask the trust whether the work counts as audit or research before you begin.
Health Visiting and the Healthy Child Programme
Health visitors lead the 0 to 5 element of the Healthy Child Programme, and local authorities in England must provide five universal reviews: antenatal (28 weeks or later), new baby (10 to 14 days), 6 to 8 weeks, 1 year and 2 to 2.5 years. GOV.UK guidance on delivering the programme was updated on 12 March 2026. For the handover from maternity care, see midwifery dissertation topics.
45. Which families miss the 2 to 2.5 year review, and what health visitors do next, analysed through the health visitor service delivery metrics
The health visitor service delivery metrics report reviews by local authority. A Master’s student could pair them with deprivation data to describe who is missed. Adding interviews would explain the numbers.
46. How health visitors use the antenatal contact at 28 weeks or later to prepare families, and how often that contact happens before birth
The antenatal contact is the first of the five reviews, but it can be the hardest to deliver. Compare local activity data with how health visitors describe their caseload planning. Report differences between areas without ranking services.
47. How health visitors use the Edinburgh Postnatal Depression Scale at the 6 to 8 week review, and what happens to a family after a high score
Follow the pathway rather than the tool: who is told, who is referred and how long it takes. A pathway mapping study with interviews fits a Master’s project. Interview mothers only with ethics approval and a distress protocol.
48. How two local authorities interpret the Healthy Child Programme guidance updated in March 2026 in their service specifications
Commissioning and delivery differ by council, so a documentary comparison can show variation. Note exactly which guidance version each council cites. This works well for an undergraduate because the documents are public.
49. What a move to a health visitor and healthy child practitioner skill mix means for continuity with a named health visitor, drawn from local authority consultation papers
Some councils have consulted on skill mix changes while keeping the five reviews under health visitor accountability. Consultation documents and committee minutes are public. Describe proposals as proposals unless a decision is recorded.
50. How health visitor students and practice assessors experience the 104 proficiencies in the NMC 2022 standards for specialist community public health nurses
Practice assessment documents list 104 proficiencies for health visiting and 109 for school nursing. Interviews with students and assessors would show which proficiencies are hard to evidence. Ask your university whether the programme’s own ethics process covers the study.
51. How fathers and non-birth parents take part in the five mandated health visitor reviews
Reviews are often arranged around mothers’ schedules. A document and interview study could examine invitation letters, appointment times and what staff say they do to involve fathers. Keep the sample diverse by family type.
52. How health visitors work with interpreters during the new baby review, and what families say is lost in translation
Home visits create practical hurdles: phone interpreting, relatives interpreting and short appointments. Observation is sensitive, so interviews with health visitors and interpreters may be the realistic option for a student.
53. How families experience the 1 year review at 9 to 15 months compared with what they expected after the 6 to 8 week contact
The review window is wide, so some families wait much longer between contacts than others. A survey in one service, with a short open-text section, could capture timing and usefulness. Use the sample size calculator to check your survey is large enough.
School Nursing and Community Children’s Nursing
School nursing teams lead the 5 to 19 element of the Healthy Child Programme, which sits alongside school nursing dissertation topics for school-based practice. The Core20PLUS5 approach for children and young people targets asthma, diabetes, epilepsy, oral health and mental health.
54. How school nurses identify unmet health needs when children start school, using the school-age stages of the Healthy Child Programme guidance
Compare the guidance with what school nurses say they do in practice and which children they miss. Document analysis plus interviews works for a Master’s project. An undergraduate can review published school nursing evaluations instead.
55. How school nurses and community children’s nurses support asthma action plans in schools in the most deprived neighbourhoods, a Core20PLUS5 priority for children and young people
Core20PLUS5 asks systems to reduce overuse of reliever medicines and cut asthma attacks. Interviews with school staff, nurses and parents could show who holds the plan and who updates it.
56. How community children’s nurses help families gain access to glucose monitors and insulin pumps, given the Core20PLUS5 aim to improve access for deprived and minority ethnic groups
A mixed-methods case study could combine technology access data from one paediatric diabetes service with interviews. NICE guideline NG18 on diabetes in children and young people gives the clinical context.
57. How school care plans for children with epilepsy are written, shared and updated, studied through document analysis and interviews with school nurses
Plans can sit in several places and go out of date. Collect anonymised templates and ask nurses how they are used in an emergency. Children’s own views matter, but involving them needs careful ethics approval.
58. How families and community paediatric teams experience waits of over 52 weeks, which affected 23.8% of children and young people on the community waiting list in June 2025
Waiting experience research would give a family-level view of what the statistics show. NHS Providers reported the figure from NHS England data. Undergraduates can analyse published parent accounts from charities and Healthwatch reports.
59. How young people with complex health needs experience the move from children’s to adult community nursing, and which handover documents helped
Transition is a known weak point, but community examples are fewer than hospital examples. A scoping review would suit an undergraduate. Interviews with young adults need careful safeguarding and consent planning.
Immunisation and Communicable Disease Control in the Community
UKHSA publishes COVER childhood vaccination data. In England, first-dose MMR coverage at age five was 91.9% in 2024 to 2025, the lowest since 2010 to 2011, against the World Health Organization target of 95%. For clinical infection topics, see infectious disease nursing dissertation topics.
60. Why MMR coverage at age five is lowest in London, and what community nursing outreach looks like in two boroughs
UKHSA’s COVER reports note that coverage varies geographically and is lowest for all antigens in London. A comparison of two boroughs, using published coverage and service descriptions, avoids the need for patient data.
61. Why the second dose of MMR lags the first, when 2023 to 2024 coverage at age five was 91.9% for one dose and 83.9% for two
The gap may reflect reminders, appointment access or other causes, and the figures cannot say which. Interview health visitors and practice nurses about how the second dose is booked and followed up.
62. How practice and community nurses talk with parents about MMR when parents are unsure, studied through detailed field notes or recorded consultations
Recording consultations needs strong ethics approval. If that is out of reach, interview nurses about the phrases they use and test them with a short vignette.
63. How the MMR catch-up campaigns of 2023 to 2024 were delivered through community nursing teams, and what they achieved in one area
The COVER report links stable five-year coverage partly to those campaigns. A local service evaluation could describe who was invited, who attended and which outreach routes worked. Start with published local reports.
64. Whether the 95% World Health Organization coverage target means much at neighbourhood level, where small numbers make local percentages unstable
A statistical project could compare coverage across small areas and show how confidence intervals widen. Use the statistical test selector to choose suitable methods.
65. How community nursing teams find and vaccinate housebound people for seasonal vaccines, and how they record people who decline
Housebound lists are often incomplete. Interview team leaders and examine how invitations, visits and declines were recorded over one season. Report counts only if the service allows access to records.
Health Inequalities and Inclusion Health in Community Health Nursing Research
NHS England’s Core20PLUS5 approach for adults defines the Core20 as the most deprived 20% of the population on the Index of Multiple Deprivation. The PLUS element covers locally identified groups, including inclusion health groups such as people experiencing homelessness, vulnerable migrants and Gypsy, Roma and Traveller communities. The adult clinical areas are maternity, severe mental illness, chronic respiratory disease, early cancer diagnosis, and hypertension case-finding with lipid management.
66. How community nursing teams decide who counts as a local PLUS group, studied through documents from two integrated care boards and interviews with nurse leaders
PLUS groups are identified locally rather than set nationally. Compare the groups named in two boards’ plans and ask nurses whether the labels match their caseloads.
67. Whether district nursing visits follow area deprivation after adjusting for age, using Community Services Data Set records and the Index of Multiple Deprivation
Core20 uses the Index of Multiple Deprivation, so the same measure fits your analysis. Data access may take months, so confirm availability with your supervisor before committing.
68. How community nurses in inclusion health teams keep continuity of care for people experiencing homelessness who move between hostels and hospitals
Qualitative case studies could track how nurses share information across services. Participants may be hard to recruit, so a staff-focused design is more realistic for a student project.
69. What barriers Gypsy, Roma and Traveller communities describe when trying to use community nursing services, drawing on published community-led research
Core20PLUS5 lists these communities among inclusion health groups. A review of community-led and charity reports is a respectful first step before any primary research. Engage with community organisations rather than approaching families directly.
70. How general practice nurses deliver annual physical health checks for people with severe mental illness, a Core20PLUS5 priority, and what stops checks being completed
The target is for annual checks to reach nationally set levels. Interviews with nurses and a review of practice-level check data could show where processes fail. For the psychiatric side, see mental health nursing dissertation topics.
71. How community nurses can support early cancer diagnosis through symptom conversations at home visits, with Core20PLUS5 aiming for 75% of cases diagnosed at stage 1 or 2 by 2028
Community nurses meet people who may delay seeking help. A small qualitative study could ask nurses when they raise symptoms with patients and how they escalate. Leave diagnostic claims to oncology resources such as oncology nursing dissertation topics.
72. Whether nurses who completed the Oliver McGowan Mandatory Training on Learning Disability and Autism report changes in the reasonable adjustments they make in community settings
The Oliver McGowan code of practice, laid in Parliament in June 2025, explains how CQC-registered providers meet the training duty in the Health and Care Act 2022. Self-report can overstate change, so combine it with examples of actual adjustments.
73. How travel time shapes the number of visits a rural district nursing team can offer, using a time-and-motion study in one health board
Travel is a hidden cost in sparse areas. Record journey times alongside clinical time for a fixed period and compare them with an urban team’s schedule. Core20PLUS also names rural and coastal communities as places where pockets of deprivation can hide.
Social Prescribing, Loneliness and Carers in Community Nursing
74. Which of the four social prescribing link worker models identified across five regions of England and Scotland fits community nursing referral pathways best
NIHR-funded work mapped four delivery models across Greater Manchester, North East and North Cumbria, West of England, Greater Glasgow and Clyde, and Lothian. A document and interview study could ask how nurses refer under each model and what feedback they receive.
75. Whether community nurses in areas with fewer link workers per 10,000 patients take on more informal social support, building on research that found geographic inequality in link worker provision
The multi-region evaluation reported uneven link worker employment across integrated care boards. Pair public workforce data with a short nurse survey, and describe results as associations.
76. How a community nurse visit becomes the main social contact for people who live alone and are housebound, explored through ethnographic field notes with consent
Ethnography takes time, so limit it to a small number of visits with clear agreements. It will be difficult within a single term. A good alternative is a review of qualitative loneliness studies among older home care users.
77. Whether community nurses refer people to green social prescribing, such as walking or gardening groups, and what stops them
An evaluation of the cross-government Green Social Prescribing programme reported statistically significant improvements in participants’ mental health. Because that evidence comes from programme evaluation, a nursing project should ask about referral practice rather than repeat the claim.
78. How family carers of people with dementia experience community nurse contact when nobody asks about their own health
More dementia ideas appear in dementia nursing dissertation topics. Interviews with carers need careful consent and support, so a review of published carer studies is the lower-risk route for undergraduates.
Heat, Housing and Climate Resilience in Community Nursing
UKHSA and the Met Office launched the Heat-Health Alerting system in June 2023, with yellow, amber and red alerts aimed mainly at health and social care. Awaab’s Law is a separate duty on social landlords in England. Position correct as of October 2026: phase 1 has applied since 27 October 2025, and phase 2 is due from 30 November 2026.
79. How community nursing teams act on yellow and amber heat-health alerts for housebound patients, studied in one community trust since the system launched in June 2023
Interviews with team leaders and a review of local heat plans could show what actually changes at each alert level. Include what happens when the alert ends.
80. How well the action cards for health and social care providers in the Heat-Health Alerting system fit the daily work of community nurses
UKHSA publishes separate action cards for commissioners, providers and the voluntary sector. Ask nurses to rate each action for practicality, then explain their ratings. This suits a Master’s project with a mixed-methods design.
81. How community nurses record and escalate hazardous housing, such as damp and mould, when Awaab’s Law sets fixed timescales for social landlords in England
Awaab’s Law covers social landlords only, not private rentals. A documentary study could trace the route from a nurse’s observation to a landlord’s repair and ask where the chain breaks. Confirm the current phase on GOV.UK before you write.
82. Whether the seven further hazards added in phase 2 of Awaab’s Law, including excess cold, falls and fire, match the risks community nurses already notice at home visits
Phase 2 widens the focus beyond damp and mould. Match the hazard list against nurses’ reports of unsafe homes in a short survey. Whether the lists match is a question for your data, not an assumption.
83. How the World Health Organization’s operational framework for climate-resilient and low carbon health systems could shape continuity plans for community nursing during flooding
Many care plans assume nurses can reach people by road. A document analysis of one trust’s emergency plan against the framework would highlight gaps for home-based patients. Keep recommendations modest, since you will not have operational data.
Digital Records and Data in Community Nursing
84. What community nurses need from the single patient record proposed in the 10 Year Health Plan to avoid repeating assessments for people seen by several teams
The plan promises a single patient record, so the enduring question is what a community nurse must see in it. Interview nurses about the information they re-ask for at each visit. Frame findings as requirements, not predictions about how the record will work.
85. How completely community nursing contacts are recorded in the Community Services Data Set compared with hospital activity data
NHS bodies have described community datasets as less mature than hospital datasets. A Master’s student could check coding completeness by contact type and region. Expect quality to vary by provider and report that variation honestly.
86. Whether hand-held devices with instant access to patient records change how community nurses and managers calculate staffing, a proposal RCN Wales has made for Welsh services
RCN Wales has argued that such devices should be standard in community nursing. A comparison of two services with and without devices, using visit logs, could test whether time on administration changes. Describe differences without implying cause unless your design supports it.
87. How integrated neighbourhood teams share patient data across health, social care and voluntary partners, a requirement the Neighbourhood Health Framework asks systems to strengthen in 2026 to 2027
Data sharing agreements and information governance shape what nurses can see. A policy analysis of two sets of local agreements, with interviews, would reveal practical hurdles. Ask the information governance team for advice before collecting any records.
Workforce, Education and Staffing Law in Community Nursing
The UK nations regulate and fund community nursing differently, so name the nation in every question you write.
88. How universities have redesigned district nurse programmes around the NMC 2022 standards of proficiency for community nursing specialist practice qualifications, using programme documents and interviews with leaders
Compare programme handbooks, then ask leaders what changed in practice assessment. The Queen’s Nursing Institute and its Scottish sister organisation also publish voluntary standards for district nurse education, which gives you a second benchmark.
89. Whether the NHS Long Term Workforce Plan goal of 1,800 district nurse training places by 2031 is realistic when 647 new students enrolled on district nurse specialist practitioner courses in 2022 to 2023
The plan aimed to raise places by 41% by 2028 and 150% by 2031. A capacity analysis could look at university placements, employer release time and funding certainty. Use Queen’s Nursing Institute education reviews for baseline numbers and update them with the most recent review.
90. How employers plan to release nurses for district nurse training when national funding for the qualification is announced late, as universities told the Queen’s Nursing Institute in its 2022 to 2023 review
Interviews with employers and universities could trace how decisions get made. Ask both groups for documents showing dates, not only opinions. This is a good fit for a Master’s student interested in workforce planning.
91. How final-year nursing students’ community placements shape their later interest in community nursing careers, responding to priority 10 of the James Lind Alliance top ten
Priority 10 asks how nurses can be encouraged to join and stay in community nursing. A small longitudinal study could follow one cohort from placement to job choice. For a single term, use a retrospective survey of recent graduates.
92. What stresses community nurses report and how clinical supervision arrangements respond, addressing priority 9 of the top ten
Use a short, validated wellbeing measure alongside interviews. Because wellbeing topics can distress participants, add signposting to support and keep identifying details out of your write-up.
93. How community nursing teams in Scotland apply the Common Staffing Method under the Health and Care (Staffing) (Scotland) Act 2019, in force from 1 April 2024
Community nursing formed part of the national staffing programme before commencement. Compare what two health boards report in their annual compliance documents. The Act is specific to Scotland, so explain that before generalising.
94. Whether the Chief Nursing Officer for Wales’s eight district nursing staffing principles can stand in for a statutory duty under the Nurse Staffing Levels (Wales) Act 2016
Section 25B covers specified inpatient wards, and Senedd research briefings described extension to district nursing as work in progress. Position correct as of October 2026: confirm the current status with the Welsh Government before writing. Frame the question around the enduring issue of principle versus law.
95. How the four UK nations differ in legislating or guiding safe staffing for community nursing, compared through legislation and official guidance
Legal commentary on Scotland’s Act describes its regulation of staffing levels as having no equivalent elsewhere in the UK. Set that against Wales’s 2016 Act and English policy documents. Add Northern Ireland only if you can verify its current position.
96. What nursing apprenticeships add to community nursing recruitment compared with university routes, following the 10 Year Health Plan’s commitment to more apprenticeships
The plan mentions more nursing apprenticeships. Compare retention and role preparedness using published apprenticeship evaluations. Treat the commitment as a stated intention until delivery data appear.
97. What stops community nurses from joining clinical academic research, given that nurses held only 8% of NIHR research awards since 2013 and community nurse-led research remains scarce
The figure comes from NIHR commentary on the Community Nursing Research Forum, hosted by the Queen’s Nursing Institute. A survey of forum members, with their permission, would test which barriers matter most.
Global Community Health Nursing and Community Health Workers
Community health nursing looks different abroad, where community health workers often deliver much of the care. These ideas use published programme evaluations, so they suit students in Pakistan, India or elsewhere. Adjust the context to your own country and check your university’s rules.
98. Whether Lady Health Workers’ doorstep services in Pakistan still raise modern contraceptive use as they did in the first national evaluation (odds ratio 1.50), tested with current Demographic and Health Survey data
Douthwaite and Ward’s 2005 evaluation found that women served by Lady Health Workers were more likely to use a modern reversible method (OR 1.50, 95% CI 1.04 to 2.16). A Master’s or PhD project could repeat the logic with newer survey rounds. Keep the comparison fair by adjusting for household and area factors, as the original did.
99. How Lady Health Workers and their supervisors describe referral to health facilities, using Oxford Policy Management evaluation reports on the National Programme for Family Planning and Primary Health Care as a starting point
The programme began in April 1994, and its evaluations report provinces separately. A secondary analysis of those reports could compare referral accounts in Sindh and Balochistan. Note the report dates so readers can see how old the evidence is.
100. Whether India’s ASHA workers still act mainly as link workers rather than community activists, following Karnataka evaluation findings from 2012
Mony and Raju found that ASHAs mostly worked as link workers and community health workers and only slightly as social activists. A newer qualitative project in one state could test whether that balance has moved.
101. Which health systems interfaces remain under-researched after Scott, George and Ved’s 2019 review of ten years of ASHA research, updated with newer studies
A systematic mapping update would suit a PhD, or a Master’s if limited to one state. State your search dates and databases clearly, and follow a reporting guideline such as PRISMA.
102. How closely three national community health worker programmes of your choice follow the 2018 WHO guideline on community health worker programmes on selection, training, supervision and integration with health systems
A comparative documentary analysis needs public programme documents, so choose countries where they exist. Explain why you chose them, because selection shapes your findings.
103. To what extent community nursing services in one country of your choice meet the three components of primary health care that WHO describes: integrated services, action on wider determinants and community participation
Use the World Health Organization definition as a scoring rubric and score evidence from national policy documents. The method suits students working outside the UK because it relies on local policy.
Worked Examples: Turning Community Nursing Dissertation Topics Into Aims and Objectives
A strong proposal pairs one aim with two or three objectives that each lead to a method. For more on structure, read how to write aims, objectives and research questions.
Example 1: Falls assessment after NICE guideline NG249
Aim: to describe how community nursing teams in one NHS trust changed falls assessment practice after NICE guideline NG249.
- Objective 1: to compare falls assessment forms used before and after April 2025.
- Objective 2: to explore team leaders’ accounts of what changed and what stayed the same.
- Objective 3: to identify barriers to referring people with gait or balance problems to falls prevention exercise programmes.
Example 2: Growth in community health service waiting lists
Aim: to describe which community service types account for the growth in adult and children’s community health service waiting lists since October 2022, and to relate the pattern to nursing-led services.
- Objective 1: to extract provider-level waiting list data from the NHS England publication.
- Objective 2: to calculate growth by service type for adults and for children and young people.
- Objective 3: to discuss implications for nursing capacity using published workforce reports.
Example 3: Hazardous housing and community nurse escalation
Aim: to explore how community nurses in one social housing area record and escalate hazardous housing conditions.
- Objective 1: to map the route from a nurse’s observation to a landlord’s response using local policies.
- Objective 2: to interview a small purposive sample of community nurses about their escalation experiences.
- Objective 3: to identify points where information is lost between nursing and housing services.
Example 4: Lady Health Workers and modern contraceptive use in Sindh
Aim: to examine whether women served by Lady Health Workers in Sindh are more likely to use a modern contraceptive method than comparable women not served.
- Objective 1: to extract and clean the relevant Demographic and Health Survey variables.
- Objective 2: to estimate the association with adjustment for household and area factors.
- Objective 3: to compare your estimate with the first national evaluation’s odds ratio and discuss differences.
How to Match Your Community Nursing Question to a Method
The research purpose should choose the method, not the other way round. A questionnaire cannot explain a complex experience, and a small interview study cannot show that a service works. If you need help weighing options, read how to choose a research methodology.
| What you want to find out | Design that tends to fit | Approval route to check first |
|---|---|---|
| How people experience a service | Qualitative interviews or focus groups | NHS staff only: HRA approval, which may not need NHS REC review. Patients: NHS REC review. Always check your university’s rules. |
| What published studies show | Scoping or systematic review | Usually no NHS ethics review. Follow your university’s rules. |
| How a service performs over time | Analysis of published statistics | Public data usually needs no NHS REC review. Identifiable records need data governance approval. |
| Whether a local change worked | Service evaluation or audit, if the trust agrees it is not research | Local trust governance rather than NHS REC review. |
Review-based projects are the most reliable route for undergraduates with short timelines. For ideas that pair well with a review, see evidence-based practice nursing dissertation topics.
Ethics and Approvals for Community Nursing Research in the NHS
In the UK, nursing research that involves NHS patients or staff usually needs more than university approval. The Health Research Authority offers decision tools in its student research toolkit: one asks whether your project counts as research, and another asks whether it needs NHS research ethics committee review.
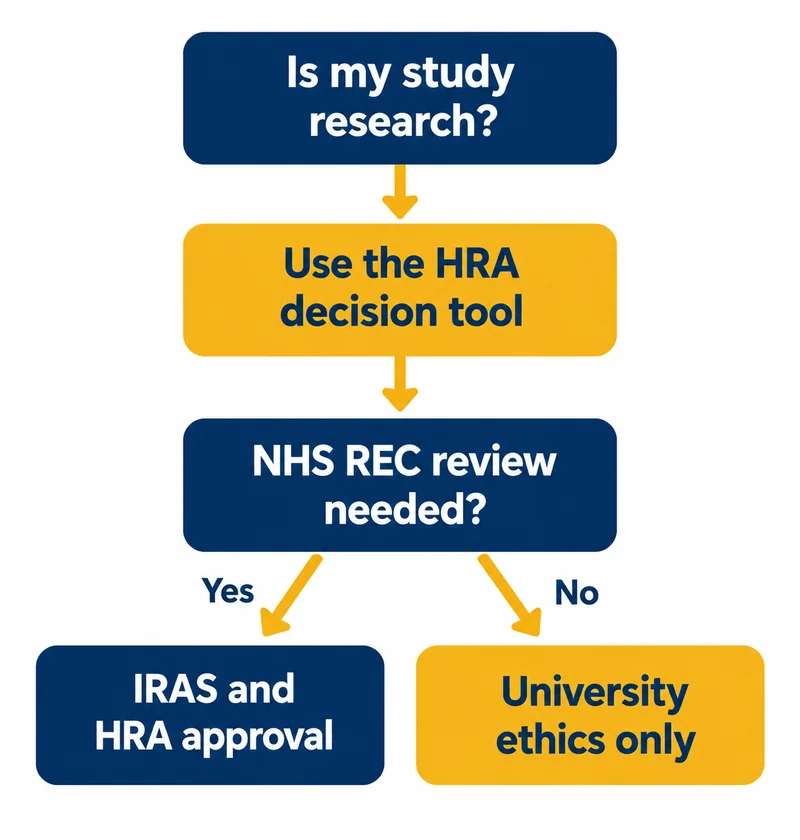
University guidance consistently describes three patterns. Studies with NHS or social care staff as participants, because of their professional role, may need HRA approval without NHS REC review, and your university may still ask for its own review. Research with adults in social care who lack capacity to consent needs review by an NHS REC that specialises in social care. Many local audits and service evaluations are not research, but the trust decides, so ask early.
Literature-based projects, scoping reviews and analyses of published statistics avoid most of these routes, which is why many supervisors steer undergraduates towards them. Our guide to ethics approval for dissertation research explains the steps and how long they can take. Because ethics rules differ by country and institution, your own university’s policy always comes first.
Where to Find Community Nursing Data and Evidence
- Service and waiting list data (England): the NHS England community health services waiting lists statistics and the Community Services Data Set.
- Child health (England): the health visitor service delivery metrics and UKHSA COVER vaccination coverage reports cited above.
- Policy documents: the 10 Year Health Plan, the Neighbourhood Health Guidelines 2025/26 and the Healthy Child Programme guidance.
- Workforce and education: Queen’s Nursing Institute education reviews and the NMC standards of proficiency.
- Scotland, Wales and Northern Ireland: Public Health Scotland, StatsWales and NISRA publish their own statistics, so name the nation in your question.
- International work: the Demographic and Health Surveys Program and the WHO Global Health Observatory suit community health worker projects.
Common Mistakes in Community Health Nursing Dissertations
- Treating community nursing as one role. District nurses, health visitors, school nurses and general practice nurses work under different standards and funding. Name the role in your title.
- Judging a programme only among people who attend. A service can look successful while missing the people who need it most. Say who was not reached.
- Applying England-only policy to the whole UK. Neighbourhood health, the 10 Year Health Plan and Awaab’s Law apply to England. Scotland and Wales have separate staffing laws and plans.
- Borrowing hospital evidence for home care without checking fit. Home visits involve lone working, shared households and carers. Test whether the evidence translates.
- Forgetting unpaid carers. Many community nursing tasks depend on family members. Include their voice or explain why not.
- Writing about proposals as settled policy. Describe draft or planned measures as such and add a dated line about the position you checked.
Frequently Asked Questions About Community Health Nursing Dissertation Topics
What are the top research topics in community health nursing?
The James Lind Alliance community nursing top ten gives a clear starting point. In rank order, it covers complex needs and multiple conditions, shared care and self-care, managing acutely ill people at home, involving unpaid carers, working with social and care services, pandemic-era changes worth keeping, continuity of the same nurse, working with hospital and specialist colleagues, nurse stress and wellbeing, and attracting and keeping community nurses.
Is community health nursing the same as public health nursing?
Not always. In the UK, health visiting, school nursing and occupational health nursing are specialist community public health roles, while district nursing and general practice nursing are community nursing roles. Programme-level questions fit public health nursing, and practice-level questions about caseloads, visits and teams fit community nursing.
Can I complete a community nursing dissertation without NHS ethics approval?
Often, yes. Reviews, document analyses and studies of published statistics avoid most NHS approval routes. Studies that involve NHS patients or staff usually need approval, so check the decision tools and your university’s rules first.
Can I use these ideas if I study outside the UK?
Yes. Pick an idea that does not rely on England-only policy, or swap in your own country’s policy documents and datasets. The global section is written for that purpose.
What is a good topic for a community health nursing presentation?
Choose one narrow idea, such as a single James Lind Alliance priority or one NICE recommendation, and explain why it matters in practice. A presentation needs one clear message, whereas a dissertation needs a question you can answer with evidence.
Next Steps for Your Community Health Nursing Research Idea
Narrow your idea with the dissertation topic finder, turn it into a question with the research question generator, then test your aims with the aims and objectives generator. The dissertation timeline planner helps you check whether the scope fits your deadline.
If you are torn between directions, revisit how to choose a research topic. For ideas outside the community setting, browse general nursing dissertation topics. Need a second pair of eyes on a shortlisted idea? Nursing dissertation help is available.
Every idea above is free to use as a starting point for your own proposal. Use any model or reference material for learning, and follow your institution’s policy on academic integrity.